

Updated April 2026. References reviewed against the 2026 ACC/AHA Dyslipidemia Guidelines.
By: Manoj K. Sharma, DO – Board Certified Internal Medicine Physician and President of Elite Medical Associates
A Heart Attack That Didn’t Have to Happen
It was 8 AM in the ER. The beeping monitors, the rushed footsteps of nurses, the controlled chaos—it was all too familiar. A 47-year-old man lay on the bed, drenched in sweat, gasping for air, his heart muscle struggling to survive. His face was pale, his body trembling, his eyes filled with terror as the crushing pressure in his chest intensified. His wife sat in the corner, frozen in shock, hands clasped together, her eyes pleading for hope.
He wasn’t supposed to be here.
Just two months earlier, he had visited his primary care doctor for a routine check-up. His labs came back with low-density lipoprotein cholesterol (LDL) of 100 mg/dL. His doctor reassured him that his numbers were “fine,” and that he had a low cardiovascular disease risk because he had no symptoms, no previous cardiac events, and no known family history of early heart disease.
His doctor followed the guidelines for the recommended LDL cholesterol level, checked the right boxes, and sent him home without medication, without further testing, and without any real assessment of his true risk.
What the Guidelines Told His Doctor to Do:
- Only target LDL-C — not LDL particle number, ApoB, or Lp(a). The assumption? LDL-C alone is enough to determine cardiovascular risk. It isn’t.
- Don’t even start checking blood cholesterol until age 35. By then, arterial plaque may already be forming, and in some cases, may already be dangerously advanced.
- No medication unless LDL-C is above 190 mg/dL or the patient has a known history of cardiovascular disease. By this logic, intervention often comes too late—after a heart attack or stroke has already occurred.
At 47 years old, this man’s heart disease had already been developing for two decades. His doctor, like many others, was following outdated guidelines—guidelines that are based on 10-year risk models, rather than a lifetime risk perspective. Based on his LDL-C alone, he didn’t “qualify” for medication—until he landed in the ER with a heart attack.
Is this good enough for you? Because it’s not good enough for me.
At Elite Medical Associates, we refuse to wait until a patient has a cardiac event before acting. We go beyond the guidelines of LDL levels to assess true cardiovascular risk before a crisis occurs. If you are claiming to practice longevity medicine but are not measuring LDL particle number (LDL-P), ApoB, and Lp(a.), what are you actually doing?
Longevity isn’t about simply extending life—it’s about preventing disease before it starts. Atherosclerotic cardiovascular disease remains the leading cause of death, and it begins decades before symptoms appear, often silently progressing until it’s too late. Yet, many physicians still rely solely on LDL-C, overlooking far more predictive markers of cardiovascular risk. If the goal of longevity medicine is to optimize healthspan, not just lifespan, then advanced lipid testing must be a foundation of any serious longevity practice—because prevention should begin long before a heart attack or stroke forces us to take action.
What is the LDL goal for cardiac patients?
For many cardiac patients, the LDL goal is below 70 mg/dL, and for those at very high risk or with established ASCVD, the goal is often below 55 mg/dL. The right target depends on your overall risk, medical history, and whether you have conditions like diabetes, so it is best to review your personal goal with your provider.
Introduction: What Is LDL Cholesterol?
For decades, medical professionals have been trained to focus on LDL cholesterol (LDL-C) as the primary target for cardiovascular disease (CVD) prevention. Statins, lifestyle modifications, and dietary interventions have all been directed toward lowering LDL-C with the assumption that low levels of LDL-C would lead to a lower risk of heart attacks and strokes. While lowering LDL-C has indeed contributed to the decline in cardiovascular events, many patients continue to suffer catastrophic cardiovascular events despite having LDL-C levels considered “normal.” Yet reaching the standard LDL goal, as defined by most guidelines, can leave significant residual risk unaddressed.
The reality is that LDL-C alone does not fully predict cardiovascular risk. Many patients with so-called “optimal” LDL-C are exposed to coronary heart disease and suffer heart attacks, while others with mildly elevated LDL-C live into old age without cardiovascular disease. This discrepancy is not an anomaly; it is a result of oversimplified risk assessment. Emerging research confirms that three markers provide a far superior assessment of atherogenic burden than LDL-C alone:
- LDL particle number (LDL-P) — counts the actual number of LDL particles, not just their cholesterol content
- Apolipoprotein B (ApoB) — a direct count of all circulating atherogenic particles
- Lipoprotein(a) [Lp(a)] — a genetically inherited, pro-inflammatory, and pro-thrombotic lipoprotein that significantly elevates cardiovascular risk
The 2026 ACC/AHA Dyslipidemia Guidelines now formally incorporate ApoB and Lp(a) measurement as key components of cardiovascular risk assessment — a meaningful step forward. However, guidelines are intended to set the minimum standard of care, not the optimal standard.
At Elite Medical Associates, we believe in staying ahead of the curve, integrating advanced management of blood cholesterol, lipid testing, genetic screening, and imaging into routine cardiovascular evaluations to ensure long-term prevention, not just short-term risk reduction, and reaching the “ideal” LDL-C goal. This article explores the limitations of LDL-C, the importance of additional biomarkers, the role of genetic testing and imaging, and a structured approach to lipid management that emphasizes lifestyle modifications before pharmacologic interventions.
Reaching Your LDL Goals Is Just the Tip of the Iceberg
For years, LDL-C has been treated as the primary metric for cardiovascular risk, leading to an oversimplified approach to lipid management. However, LDL-C only measures the cholesterol content within LDL particles, not the actual number of LDL particles themselves. This distinction is critical because it is the number of particles, rather than the total cholesterol mass, that determines the likelihood of arterial plaque formation.
To understand this, imagine two different highways filled with cars. One highway has 10 large trucks carrying the same amount of cargo, while another has 50 smaller cars carrying an equivalent load. While both highways transport the same total cargo, the highway with more cars is more congested and more prone to accidents. In this analogy, LDL-C measures the total cargo, while LDL particle number (LDL-P) counts the number of vehicles on the road. The more particles there are, the greater the chance of arterial injury and plaque formation, regardless of the total cholesterol carried by those particles.
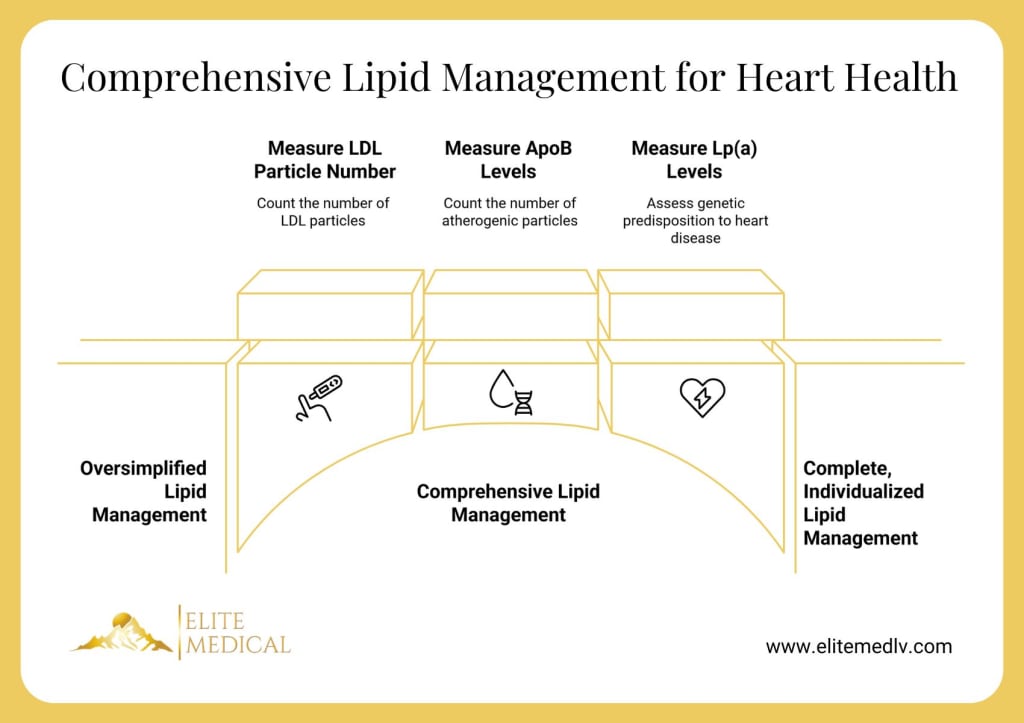
Several major studies, including the UK Biobank Study and research by Sniderman AD in Circulation, have confirmed that patients with normal LDL-C but elevated ApoB or LDL-P are at significantly higher risk of cardiovascular events. Many individuals who have a low or moderate LDL-C level are falsely reassured by their lab results, when in fact, they have a high burden of small, dense LDL particles that aggressively contribute to atherosclerosis.
ApoB is a superior marker because each atherogenic lipoprotein (LDL, VLDL, Lp(a)) contains a single ApoB molecule, making it a direct count of the number of circulating atherogenic particles. Unlike LDL-C, which can fluctuate due to dietary intake, hydration status, or even recent exercise, ApoB remains a stable and reliable measure of risk.
Beyond LDL-P and ApoB, Lp(a) is another often-overlooked but critically important risk factor. Lp(a) is genetically inherited and has a pro-inflammatory and pro-thrombotic effect, significantly increasing the risk of heart disease and stroke. Lp(a) levels remain relatively stable throughout life, meaning that measuring Lp(a) once provides a lifelong indicator of genetic risk. Despite its well-documented role in cardiovascular disease, Lp(a) is not routinely measured in many clinical settings, leaving many high-risk individuals unaware of their predisposition.
If our goal is true prevention of coronary heart disease, we must move beyond LDL-C alone as the gold standard and incorporate a more complete, individualized approach to lipid management.
How Low Should Your LDL Goal Be?
Recent research suggests that lowering LDL to ultra-low levels (<20 mg/dL) provides substantial additional benefits with no apparent safety concerns. This is one of the hottest debated topics in lipidology. While earlier guidelines suggested an LDL goal of around 70 mg/dL for high-risk individuals, the evidence for going lower has become increasingly compelling.
The FOURIER Trial, ODYSSEY Outcomes Trial, and IMPROVE-IT Trial have all demonstrated that the lower the LDL-C, the greater the reduction in risk of coronary heart disease and cardiovascular events. The idea that excessively low LDL-C might be harmful has been debunked by genetic studies on people with PCSK9 loss-of-function mutations. These individuals have lifelong LDL-C levels below 20 mg/dL and experience drastically lower rates of cardiovascular disease without adverse effects.
Importantly, LDL-C does not operate in isolation. While ultra-low LDL-C reduces cardiovascular risk, combining LDL reduction with Lp(a) monitoring and aggressive control of metabolic factors provides even greater protection. For example, patients with high Lp(a) may still require even lower LDL targets to counteract their genetically elevated risk.
Additionally, the duration of LDL exposure matters. Patients who start with high cholesterol in early adulthood may need aggressive treatment to reverse decades of plaque buildup, whereas individuals with low lifetime LDL exposure may require less intensive therapy. The key takeaway is that lower is better, but personalized treatment is crucial.
When Should We Start Cholesterol Screening?
Screening should begin earlier than current guidelines recommend — ideally in childhood for high-risk individuals. One of the biggest flaws in current lipid management is the delayed onset of screening. If cardiovascular disease is often asymptomatic for decades before manifesting as a heart attack or stroke, why do most guidelines still recommend starting cholesterol screening at age 35 or later?
Studies of young accident victims have shown early arterial plaque formation in children as young as 10 years old, particularly those with obesity, insulin resistance, or a strong family history of heart disease. This suggests that atherosclerosis is a decades-long process, not a condition that suddenly appears in middle age.
Current pediatric guidelines recommend universal lipid screening between ages 9-11 and again between ages 17-21. However, for children with metabolic syndrome, obesity, or a family history of early cardiovascular disease, screening should begin even earlier. Identifying high-risk individuals in childhood allows for early lifestyle interventions that can prevent long-term disease progression.
If we truly aim to prevent cardiovascular disease, we must rethink our approach to screening and intervention, shifting toward earlier detection and earlier treatment.
What is LDL-C lowering, and why does it matter?
LDL-C lowering means reducing low-density lipoprotein cholesterol to help protect your heart and blood vessels. It can be especially important for people with diabetes or those needing secondary prevention after a cardiac event. Along with improving HDL cholesterol, also known as high-density lipoprotein, this approach supports better cardiovascular health and aligns with guidance from the American Heart Association.
Is Lifestyle Modification Enough to Protect Against Heart Disease?
Lifestyle modification should always precede pharmacotherapy — it is the foundation of cardiovascular prevention and is nearly always safe. Before initiating pharmacologic treatment, it is essential to optimize lifestyle interventions, as multiple landmark studies have demonstrated that diet, exercise, and weight loss can significantly improve lipid profiles and reduce long-term cardiovascular risk.
The PREDIMED Trial, which examined the Mediterranean diet, found that adopting a diet rich in healthy fats, fiber, and polyphenols can lower LDL-C by 10-15% and reduce cardiovascular mortality. The Framingham Heart Study and AHA Exercise Guidelines have confirmed that consistent physical activity reduces LDL-C, improves insulin sensitivity, and lowers inflammation.
Patients often ask whether lifestyle changes alone are enough. For some, particularly those with mild lipid abnormalities and no additional risk factors, lifestyle alone may be sufficient. However, for individuals with genetic hypercholesterolemia, high Lp(a), or existing arterial plaque, medications provide an essential additional layer of protection.
By starting with diet, exercise, and metabolic optimization, patients can achieve significant cardiovascular benefits with minimal risk. Only when lifestyle interventions are insufficient should pharmacotherapy be added as a step-up intervention.
When to Start Statin Treatment?
Once lifestyle interventions are optimized, the next question is when pharmacologic therapy is needed to reach a more aggressive LDL goal. For individuals at high cardiovascular risk, lifestyle modifications alone may not be enough to fully mitigate their atherogenic burden. In these cases, pharmacologic therapy becomes a necessary tool, not as a replacement for lifestyle interventions but as an additional safeguard against ongoing disease progression. However, not all lipid-lowering medications are created equal, and treatment must be tailored based on the specific lipid abnormalities present.
Statins remain the first-line therapy for lowering LDL-C, as they have been extensively studied and consistently shown to contribute to the prevention of cardiovascular events. By inhibiting HMG-CoA reductase, statins decrease the liver’s production of cholesterol, leading to a 30-60% reduction in LDL-C levels and a significant decrease in cardiovascular risk. They also have pleiotropic benefits, including reducing vascular inflammation and stabilizing plaques, which further contribute to their protective effects.
For patients requiring additional LDL lowering beyond statins, the following step-up options are available:
- Ezetimibe — blocks intestinal cholesterol absorption; provides an additional 15–20% reduction in LDL-C; useful for statin-intolerant patients or those needing more aggressive control
- PCSK9 inhibitors (evolocumab, alirocumab) — most potent option; 45–60% additional LDL-C reduction plus corresponding ApoB reduction; supported by FOURIER and ODYSSEY Outcomes trials
- Bempedoic acid / Berberine — for statin-intolerant patients; bempedoic acid inhibits cholesterol synthesis upstream of the HMG-CoA pathway; berberine reduces LDL by 15–25% and improves insulin sensitivity
- Emerging Lp(a) therapies — antisense oligonucleotides and siRNAs currently in trials; showing 20–80% Lp(a) reduction; niacin has historically been used but cardiovascular benefit remains uncertain
Ultimately, medications should be viewed as a tool to enhance, not replace, lifestyle-based prevention strategies. A multifactorial approach—one that addresses not just LDL-C but also LDL-P, ApoB, and Lp(a)—offers the greatest level of protection against cardiovascular events.
Is lifestyle modification enough to protect against heart disease?
For some patients — particularly those with mild lipid abnormalities and no additional risk factors — lifestyle modification alone may be sufficient. The PREDIMED Trial demonstrated that a Mediterranean diet can lower LDL-C by 10-15% and reduce cardiovascular mortality. However, for individuals with genetic hypercholesterolemia, high Lp(a), or existing arterial plaque, medications provide an essential additional layer of protection that lifestyle alone cannot replace.
When and How to Step Down Treatment
While much of lipid management focuses on intensifying therapy, we must also recognize situations where it may be appropriate to de-escalate treatment. Patients who achieve long-term lipid control, maintain optimal metabolic health, and exhibit no signs of disease progression may be candidates for medication tapering under careful supervision.
Deprescribing should be approached with caution, as atherosclerosis is a chronic, progressive condition. Even when plaque stabilization or regression has been achieved, discontinuing medication too soon can allow the disease process to reactivate, potentially undoing years of progress.
The process of step-down therapy should involve:
- Continued risk assessment: Patients should undergo periodic ApoB, LDL-P, and Lp(a) testing to ensure that their risk profile remains stable before reducing medication doses.
- Imaging follow-up: Coronary artery calcium (CAC) scoring and carotid intima-media thickness (CIMT) scans can be used to track disease regression or stability, helping to determine whether medication de-escalation is appropriate.
- Gradual dose reduction: Rather than abruptly stopping lipid-lowering medications, a stepwise reduction in dosage allows for monitoring of any rebound effect in cholesterol levels.
- Continued lifestyle adherence: Patients who discontinue medication must maintain strict adherence to dietary and exercise recommendations to ensure sustained lipid control.
Some individuals may successfully transition to lifestyle-only maintenance, while others may require lifelong pharmacologic support based on their genetic risk, arterial plaque burden, and long-term lipid trends. The key is personalization—there is no universal approach to deprescribing, just as there is no universal approach to initiating therapy.
When Should Genetic Testing and Imaging Be Used in Cardiovascular Risk Assessment?
For some individuals, standard lipid testing is insufficient to fully assess cardiovascular risk. In these cases, genetic testing and advanced imaging provide additional tools to detect high-risk patients early, long before symptoms develop.
Polygenic Risk Scores (PRS) offer a modern approach to assessing inherited cardiovascular risk. Unlike traditional genetic testing, which focuses on single-gene mutations, PRS evaluates thousands of genetic variants associated with coronary artery disease, Lp(a) levels, and cholesterol metabolism. By incorporating genetic risk into clinical decision-making, physicians can identify individuals who may require early and aggressive intervention, even if their traditional risk factors appear mild.
Beyond genetics, advanced imaging plays a crucial role in assessing subclinical atherosclerosis. Coronary artery calcium (CAC) scoring is one of the most predictive tools for determining actual plaque burden, helping to distinguish between patients who can benefit from aggressive lipid lowering versus those who may not require immediate intervention. CT angiography (CTA) allows for direct visualization of coronary arteries, identifying plaques and stenosis before symptoms occur.
For patients with borderline cholesterol levels or uncertain risk, these tools provide essential information for guiding long-term prevention strategies. By incorporating genetic screening and imaging alongside traditional lipid testing, we can detect disease early, tailor interventions appropriately, and prevent cardiovascular events before they happen.
Conclusion
For years, cardiovascular prevention has been centered around LDL-C reduction, but the latest research confirms that LDL alone is not enough. Advanced lipid markers—including ApoB, LDL-P, and Lp(a)—offer a more accurate assessment of cardiovascular risk, allowing for earlier intervention and more personalized treatment strategies.
At Elite Medical Associates, we employ cutting-edge diagnostics, genetic screening, and imaging to provide a proactive, rather than reactive, approach to cardiovascular health.
Our strategy is not just about managing disease—it is about preventing it entirely. By emphasizing lifestyle interventions first, utilizing precise pharmacologic strategies when necessary, and integrating advanced diagnostic tools, we are able to optimize cardiovascular health for the long-term, not just the next ten years.
As cardiovascular prevention evolves, we must move beyond LDL-C as a single measure of risk and embrace a more comprehensive, personalized approach. The future of medicine is not just about lowering cholesterol—it is about understanding the entire cardiovascular picture, treating early, and preventing disease before it ever has the chance to develop.
For those looking to take control of their cardiovascular health, a thorough lipid evaluation, genetic risk assessment, and advanced imaging workup can provide the insights needed to personalize treatment strategies. Whether through lifestyle, medication, or a combination of both, the goal remains the same: long-term protection from heart disease and a healthier future.
For an advanced cardiovascular risk assessment, call (702) 291-8511. Your future self will thank you.
This article is for informational purposes only and is not intended as medical advice. The information provided here should not be used to diagnose, treat, cure, or prevent any disease. Always consult a qualified healthcare professional before making any changes to your medical treatment, diet, or lifestyle. The recommendations discussed in this article are based on current research and expert consensus but should be tailored to individual patient needs in consultation with a physician.
References
- Ference BA, Graham I, Tokgozoglu L, Catapano AL. Impact of lipoprotein(a) on cardiovascular risk and the need for new therapies. Eur Heart J. 2022;43(39):3961-3972.
- Sniderman AD, Thanassoulis G, Williams K, et al. Why ApoB is superior to LDL in predicting cardiovascular risk. Circulation. 2019;139(5):572-581.
- Emerging Risk Factors Collaboration, Di Angelantonio E, Gao P, et al. Lipid-related markers and cardiovascular disease prediction. JAMA. 2012;307(23):2499-2506.
- UK Biobank Study. Discordance between LDL, non-HDL, and ApoB in cardiovascular risk assessment. JAMA Cardiol. 2020;5(6):672-680.
- FOURIER Trial Investigators, Sabatine MS, Giugliano RP, Keech AC, et al. Evolocumab and clinical outcomes in patients with cardiovascular disease. N Engl J Med. 2017;376(18):1713-1722.
- ODYSSEY Outcomes Investigators, Schwartz GG, Steg PG, Szarek M, et al. Alirocumab and cardiovascular outcomes after acute coronary syndrome. N Engl J Med. 2018;379(22):2097-2107.
- IMPROVE-IT Investigators, Cannon CP, Blazing MA, Giugliano RP, et al. Ezetimibe added to statin therapy after acute coronary syndromes. N Engl J Med. 2015;372(25):2387-2397.
- PREDIMED Study Investigators, Estruch R, Ros E, Salas-Salvadó J, et al. Primary prevention of cardiovascular disease with a Mediterranean diet. N Engl J Med. 2013;368(14):1279-1290.
- AHA Scientific Statement. Physical activity and cardiovascular health. Circulation. 2020;141(5):e595-e619.