
Guide to Hormonal Health and Rest
Written by Dr. Manoj Sharma, DO, Founder and President of Elite Medical Associates, a leader in evidence-based internal medicine, longevity-focused precision care.
Why Testosterone and Sleep Are Closely Linked
In the landscape of human physiology, few feedback loops are as powerful—and as underappreciated—as the relationship between testosterone and sleep. Testosterone, often mischaracterized as simply the “male hormone,” is in truth a vital anabolic signal for both men and women, shaping energy, mood, strength, bone health, cognition, and even vascular integrity. Sleep, meanwhile, is the deeply restorative process that synchronizes circadian rhythms, consolidates memory, and recalibrates the endocrine system.
The striking reality is this: poor sleep suppresses testosterone, and low testosterone disrupts sleep. This bidirectional cycle explains much of the fatigue, weight gain, mood instability, and metabolic dysfunction we see in midlife patients. Just one week of restricted sleep (five hours per night) reduces daytime testosterone by 10–15% in healthy young men—an effect comparable to aging 10-15 years (Leproult & Van Cauter, JAMA 2011). Conversely, men with clinically low testosterone frequently report insomnia, restless nights, reduced REM sleep, and chronic fatigue. Women, especially in perimenopause and postmenopause, likewise experience profound changes in sleep quality when androgen levels fall.
At Elite Medical Associates, we emphasize this interplay because it represents more than just symptom management. It is about restoring the physiologic rhythm of vitality. Optimizing both testosterone and sleep has cascading benefits for metabolism, cognitive longevity, cardiovascular protection, and quality of life. To ignore one while treating the other is to miss the bigger picture of healthspan medicine.
Understanding Testosterone: The Vital Hormone
What is Testosterone?
Testosterone is a C19 steroid hormone, derived from cholesterol through a tightly regulated series of enzymatic steps. The Leydig cells of the testes (in men) produce~95% of circulating testosterone, while in women, smaller amounts come from the ovaries and adrenal cortex.
Production is orchestrated by the hypothalamic-pituitary gonadal (HPG) axis:
- The hypothalamus secretes gonadotropin-releasing hormone (GnRH) in pulses.
- GnRH stimulates the anterior pituitary to release luteinizing hormone (LH).
- LH binds Leydig cells, activating steroidogenesis and testosterone synthesis.
Circulating testosterone exists in three states:
- Free testosterone (~2–3%) – biologically active.
- Albumin-bound testosterone – loosely bound, bioavailable.
- Sex hormone-binding globulin (SHBG)-bound testosterone – tightly bound, not bioavailable.
Functions of Testosterone in Men and Women
In men, testosterone regulates:
- Muscle growth & strength via androgen receptor activation.
- Bone density by stimulating osteoblast activity.
- Erythropoiesis and hemoglobin regulation.
- Libido and erectile function.
- Cognition and mood, particularly motivation and spatial processing.
In women, testosterone contributes to:
- Ovarian follicle development.
- Sexual desire and arousal.
- Energy, resilience, and vitality.
- Mood stabilization.
- Skeletal integrity in synergy with estrogen.
Factors Influencing Testosterone Production
Testosterone levels are influenced by:
Age: Decline ~1% annually after age 30 in men.
Sleep: Consolidated slow-wave sleep drives peak
secretion.
Stress & cortisol: Chronic cortisol suppresses GnRH.
Nutrition: Adequate protein, zinc, vitamin D,
omega-3s are essential.
Exercise: Resistance training acutely elevates T.
Metabolic conditions: Obesity, insulin resistance, and
diabetes strongly suppress testosterone.
Inflammation: Cytokines like TNF-α impair Leydig
cell steroidogenesis.
The Science of Sleep and Its Stages
Sleep is not passive—it is an active neuroendocrine state governed by the brain’s circadian pacemaker (suprachiasmatic nucleus) and regulated by neurotransmitters (GABA, adenosine, orexin) and hormones (melatonin, cortisol).
The Role of Deep Sleep and REM Sleep
NREM stage 3 (slow-wave sleep) is when testosterone and growth hormone secretion peak.
REM sleep consolidates memory and is associated with nocturnal erections in men, reflecting androgen sufficiency.
Hormonal Regulation During Sleep
- Melatonin from the pineal gland aligns circadian rhythms and indirectly influences GnRH secretion.
- Growth hormone surges in parallel with testosterone during early-night slow-wave sleep.
- Cortisol follows an inverse rhythm, falling at night and rising before dawn. Poor sleep elevates cortisol, suppressing testosterone further.
Sleep, therefore, is not simply restorative—it is fundamentally anabolic.
How Testosterone and Sleep Interact
The Sleep-Testosterone Feedback Loop
Good sleep → ↑ testosterone → improved sleep depth.
Poor sleep → ↓ testosterone → more fragmented sleep.
This loop can spiral upward in health or downward in dysfunction.
Peak Testosterone Levels and Circadian Rhythms
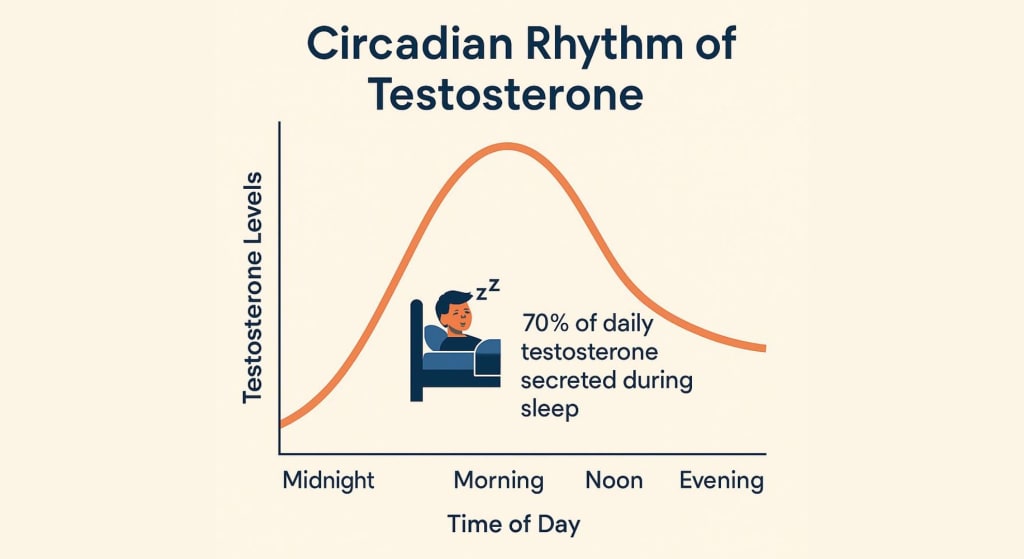
Testosterone peaks in the early morning (7–10 AM) after consolidated sleep. Sleep deprivation blunts this rhythm, flattening the diurnal curve and mimicking premature aging.
Testosterone Production During Sleep Cycles
Over 70% of daily testosterone is secreted during sleep, primarily during the first 3 hours of uninterrupted slow wave sleep. Sleep fragmentation interrupts this secretion, even if total sleep time appears adequate.
Effects of Poor Sleep on Testosterone
Sleep Deprivation and Hormonal Decline
A week of restricted sleep (5h/night) in healthy men caused a 15% drop in testosterone and impaired vigor, mood, and libido (Leproult & Van Cauter, JAMA 2011). This demonstrates how even modest, chronic sleep restriction mimics hypogonadism.
Sleep Apnea and Testosterone Deficiency
Obstructive sleep apnea (OSA) disrupts testosterone
through:
- Hypoxia → oxidative stress in Leydig cells.
- Fragmented sleep → impaired GnRH pulsatility.
- Inflammation → suppression of steroidogenesis.
Men with OSA consistently have lower testosterone. Treatment with CPAP restores testosterone in some but not all patients (Cistulli & Grunstein, Sleep 1996).
Long-Term Sleep Loss and Hypogonadism
Chronic insomnia and shift work elevate IL-6 and TNF-α, reduce testicular sensitivity to LH, and disrupt circadian rhythms. Over time, this contributes to late-onset hypogonadism.
Effects of Low Testosterone on Sleep Quality
Insomnia and Restlessness
Men with low testosterone often describe difficulty falling asleep and frequent awakenings.
Reduced REM Sleep
Low testosterone reduces REM density and nocturnal erections, impairing neurocognitive recovery.
Night Sweats, Mood Changes, and Fatigue
Symptoms mimic classic sleep disorders—vasomotor instability, irritability, and nonrestorative fatigue—making hormonal evaluation essential in sleep clinics.
Clinical Research on Testosterone and Sleep
- Penev, JAMA 2007: Men with <6h sleep had 15% lower testosterone than peers sleeping 7–8h.
- Andersen, JCEM 2016: Testosterone rises during consolidated sleep, not wakeful rest.
- Meta-analyses: TRT improves vitality but shows mixed results on objective sleep measures.
- OSA studies: CPAP improves testosterone variably; weight loss remains the strongest modifier.
Testosterone Replacement Therapy (TRT) and Sleep
Can TRT Improve Sleep Quality?
TRT improves libido, energy, and subjective sleep quality in men with hypogonadism. Some studies show increased slow-wave sleep after testosterone restoration.
Risks of TRT and Sleep Apnea Worsening
However, TRT may worsen OSA by:
- Relaxing upper airway muscles.
- Increasing hematocrit and oxygen demand.
- Reducing ventilatory drive in predisposed men.
Medical Guidelines for TRT and Sleep Disorders
- Endocrine Society: Testosterone only in men with symptoms and consistently low levels. Evaluate for OSA before initiation.
- AUA: Emphasizes baseline and follow-up hematocrit and sleep assessments.
- Clinical pearl: Always screen high-risk men (obese, snoring, daytime sleepiness) with a sleep study before TRT.
Natural Ways to Boost Testosterone and Improve Sleep
Sleep Hygiene and Restorative Habits
- Maintain consistent bed/wake times.
- Dark, cool, quiet environment.
- Avoid blue light and late meals.
- Target 7–9 hours of consolidated sleep.
Nutrition and Supplements
- Zinc, magnesium, vitamin D: critical cofactors for testosterone and sleep.
- Omega-3 fatty acids: reduce inflammation and support REM sleep.
- Ashwagandha: RCTs show increases in testosterone and improved sleep quality.
- Tongkat Ali: modest T improvements in stressed men.
- Shilajit: A mineral-rich resin studied in Indian and Nepalese populations. Human RCTs show increased total and free testosterone, improved mitochondrial function, and enhanced vitality. Emerging data suggest improved sleep quality through stress reduction and circadian regulation.
Exercise and Stress Management
- Resistance training: consistently raises testosterone.
- HIIT: effective but avoid overtraining.
- Mindfulness and meditation: reduce cortisol, indirectly benefiting both T and sleep.
Polygenic and Genomic Influences on Sleep and Testosterone
The interplay between sleep and testosterone is strongly gene-modulated.
- Clock genes: Variants in PER3, CLOCK, BMAL1 influence circadian preference (morningness/eveningness) and sleep duration. These in turn affect testosterone rhythms.
- Androgen receptor CAG repeats: Shorter repeats increase receptor sensitivity, influencing sleep quality and vitality.
- SHBG polymorphisms: Alter free testosterone availability, impacting both sleep and symptoms.
- CYP19A1 (aromatase): Variants influence estrogen:testosterone ratio, affecting sleep stability.
Genomic testing offers future promise: tailoring TRT and sleep interventions to a patient’s polygenic risk profile. At Elite Medical Associates, we already integrate such testing to guide individualized care.
Special Populations
Aging Men
Andropause overlaps with increasing sleep fragmentation. Differentiating normal aging from hypogonadism is crucial.
Women
Low testosterone in women (post-oophorectomy,
menopause) is linked with poor sleep and fatigue.
Carefully monitored low-dose androgen therapy can help.
Athletes
Overtraining suppresses testosterone and disrupts sleep. Monitoring recovery biomarkers is key.
Shift Workers
Circadian misalignment flattens testosterone rhythms. Strategic light therapy, anchor sleep, and melatonin can mitigate risks.
When to Seek Medical Help
Symptoms of low testosterone and poor sleep often overlap:
- Fatigue, low energy.
- Decreased libido.
- Depressed mood.
- Insomnia or restless nights.
Testing: Morning testosterone (7–10 AM), free T, SHBG, LH/FSH. Consider sleep study for suspected OSA.
Team-based care: Endocrinologists, sleep physicians, and integrative clinicians collaborating is best practice.
Expanded FAQs
Does napping affect testosterone?
Short naps may restore alertness but do not meaningfully increase testosterone. Only deep nocturnal sleep drives secretion.
How quickly does sleep loss lower testosterone?
Within 5–7 days of restriction, declines are measurable. Chronic deficits amplify the effect.
Do melatonin or magnesium help testosterone?
Melatonin improves sleep quality, indirectly supporting T. Magnesium supplementation improves free testosterone in deficient men.
Is it safe for women to take testosterone for sleep?
In selected cases (postmenopausal, oophorectomized women with low T), carefully dosed therapy can improve vitality and sleep.
What’s the relationship between cortisol, testosterone, and sleep?
Chronic insomnia elevates cortisol, which suppresses GnRH and lowers T. Conversely, balanced testosterone promotes deeper sleep and helps regulate cortisol rhythms.
Clinician’s Corner
- Lab timing: Always measure testosterone 7–10 AM, after consolidated sleep.
- TRT initiation: Baseline sleep study in men at risk for OSA.
- Red flags: Low T with low/normal LH & FSH → evaluate for pituitary disease.
- Adjuncts: Sleep diaries, actigraphy, and genomic profiling enhance diagnostic precision.
Conclusion: Optimizing Testosterone and Sleep for Long-Term Health
Testosterone and sleep are inseparable pillars of healthspan. Neglecting one inevitably destabilizes the other, leading to fatigue, obesity, depression, cardiometabolic disease, and accelerated aging. But when optimized together, they create a virtuous cycle of resilience, vitality, and longevity.
At Elite Medical Associates, we emphasize that sleep is anabolic medicine and testosterone is its hormonal amplifier. Through precision diagnostics, lifestyle interventions, genomic personalization, and—when appropriate—carefully guided TRT, we restore the physiologic rhythms that sustain human health.
The future of medicine is not disease management. It is about honoring and restoring the body’s natural cycles— synchronizing sleep, hormones, and genetics—to unlock both lifespan and healthspan